Why is deciding when to remove a tracheostomy particularly challenging in patients recovering from brain injury, and what are the risks of removing it too early or keeping it for too long?
For someone recovering from an acquired brain injury, removal of a tracheostomy tube can be an important step in rehabilitation. The difficult part is deciding when the person is ready. Breathing comfortably is only one part of the decision. The person also needs to manage secretions, protect the airway during swallowing and have adequate upper-airway and laryngeal function. Brain injury can affect several of these functions at the same time, and recovery does not occur at the same rate in every patient. A person may therefore appear clinically stable but still have difficulty clearing secretions or protecting the airway. Removing the tube too early can lead to respiratory deterioration, airway compromise, aspiration or the need for recannulation. On the other hand, leaving the tube in place longer than necessary can prolong exposure to tracheostomy-related problems and may interfere with communication, swallowing and participation in rehabilitation. The practical question is therefore: is this particular patient ready to breathe, clear secretions and protect the airway safely without the tracheostomy?
Your research explores a structured bedside approach for determining whether a patient is ready for tracheostomy removal. Could you explain how this approach works in simple terms?
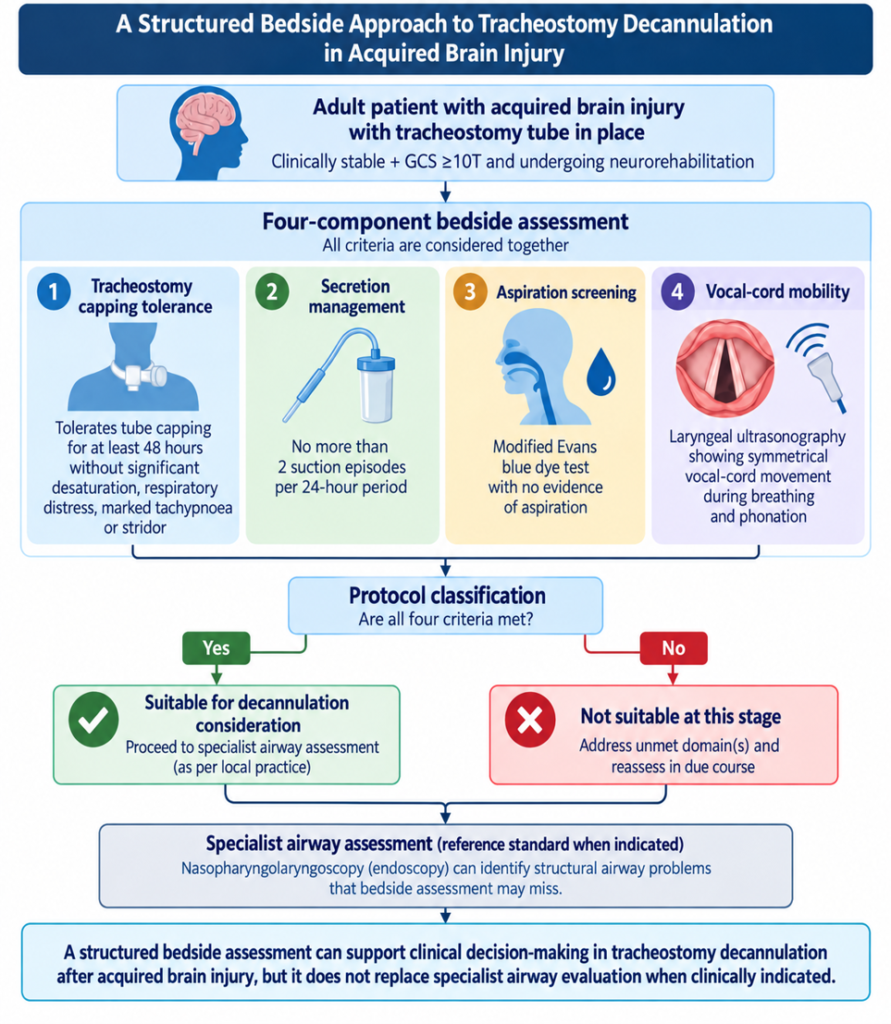
We wanted to see whether several relatively simple bedside observations could be brought together into a structured assessment. We prospectively studied 36 adults with chronic acquired brain injury undergoing neurorehabilitation. The protocol looked at four areas: how well the patient tolerated tracheostomy capping, how often suctioning was required, whether there was evidence of aspiration on a modified Evans blue dye test, and whether the vocal cords moved symmetrically on laryngeal ultrasound. For capping, participants were observed for at least 48 hours. Significant oxygen desaturation, respiratory distress, marked tachypnoea, or stridor were considered reasons not to pass this part of the assessment. Suction requirements were recorded prospectively, with no more than two suction episodes per 24-hour period required during the observation period. The four findings were considered together. We then compared the bedside classification with a blinded nasopharyngolaryngoscopic examination performed by otolaryngologists. In simple terms, the protocol was designed to provide a consistent bedside way of assessing whether a patient appeared suitable for further consideration of decannulation, rather than relying on a single sign or test. It was intended to support clinical decision-making, not replace specialist airway assessment when this was clinically indicated.
Laryngeal ultrasound is an important part of this approach. What can it reveal about a patient’s vocal cords and airway, and what advantages does it offer as a non-invasive bedside tool?
Laryngeal ultrasound allows the movement of the vocal cords to be observed through the skin of the neck. In our study, a trained radiologist used a high-frequency linear probe to assess whether the vocal cords opened and closed symmetrically during breathing and phonation. The main practical advantage is that it is non-invasive and can be performed at the bedside. It does not require an endoscope to be passed through the nose or throat, and the assessment can potentially be repeated when needed. This may be particularly useful in rehabilitation settings where specialist endoscopic assessment is not immediately available. There are also limitations. Ultrasound does not provide the same direct view of the airway that endoscopic examination provides. Image quality and interpretation can also depend on the patient and the operator’s experience. For this reason, we used ultrasound as one component of a four-part protocol. Our study does not show that laryngeal ultrasound alone can determine whether a patient is ready for decannulation.
The bedside protocol showed 96% sensitivity and about 92% overall accuracy compared with specialist airway examination. What do these findings mean from a clinical perspective?
Of the 36 participants, 25 were considered suitable for decannulation according to the reference nasopharyngolaryngoscopic assessment. The bedside protocol identified 24 of these 25 participants, corresponding to a sensitivity of 96%. Overall, the bedside classification agreed with the specialist assessment in 33 of the 36 participants, giving an accuracy of 91.7%. Specificity was 81.8%, and the Cohen’s kappa value was 0.80, indicating substantial agreement in this cohort. In clinical terms, these findings suggest that the protocol was able to identify most of the participants who were considered suitable for decannulation by the reference assessment. At the same time, these findings come from a relatively small, single-center study involving 36 patients. The confidence intervals around some of the estimates were wide. The results should therefore be viewed as evidence of potential usefulness rather than proof that the bedside protocol is equivalent to endoscopic assessment.
Could this type of bedside assessment be particularly useful in hospitals and rehabilitation centres where access to specialists or endoscopic examinations is limited?
There is a potential practical role for this type of assessment in these settings. A structured approach can help clinicians consider the same important factors in a consistent way, even when an otolaryngology service or endoscopic examination is not immediately available. This could be particularly relevant in neurorehabilitation, where patients may remain in rehabilitation facilities for prolonged periods and decisions about tracheostomy management are made as neurological recovery progresses. However, our study did not measure costs, specialist referral rates, procedure utilisation, or health-system outcomes. We therefore cannot conclude from this study that the protocol reduces resource use or replaces specialist services. A reasonable way to view the protocol is as a bedside assessment and decision-support approach. It may help clinicians identify patients who appear suitable to proceed to the next stage of assessment, while patients with concerning or uncertain findings can be referred for specialist evaluation.
Your study also identified situations where bedside assessment could miss structural airway problems. What does this tell us about the continued role of endoscopy and specialist evaluation?
This was one of the clearest lessons from the study. Two participants passed the bedside protocol but were found on nasopharyngolaryngoscopy to have suprastomal granulation tissue causing approximately 50% narrowing of the airway. These structural abnormalities were not detected by the bedside assessment. This illustrates the difference between assessing whether a patient appears physiologically ready for decannulation and directly examining the airway. A bedside assessment can provide useful information about breathing, secretion management, aspiration risk, and vocal-cord movement, but it cannot identify every structural abnormality. The findings therefore support a complementary approach. Endoscopy remains important when structural airway disease is suspected, when bedside findings do not fit the clinical picture, or when there is uncertainty about whether decannulation is appropriate. In our study, the bedside protocol was intended to support clinical decision-making, not to replace specialist airway examination when it is clinically indicated.
Looking ahead, how do you see this approach influencing tracheostomy care and neurorehabilitation, and what further research is needed before it can be adopted more widely?
The main potential value of this approach is not a new single test, but a more structured way of bringing several bedside observations together. In neurorehabilitation, decannulation is part of a wider process of recovery involving breathing, airway protection, swallowing, communication, and participation. Our study provides an initial prospective evaluation of the composite protocol against blinded specialist airway assessment. It does not establish whether using the protocol improves long-term rehabilitation outcomes or reduces healthcare utilisation. Before the approach can be used more widely, it needs to be tested in larger and more diverse patient populations and across multiple centers. Future studies should also examine how consistently different clinicians can perform and interpret the ultrasound assessment, how much each component contributes to the overall result, and how the protocol performs in different rehabilitation and acute-care settings. The message from our study is therefore fairly simple: a structured bedside assessment may help clinicians identify patients who are ready for consideration of decannulation, but it should complement clinical judgement and specialist airway assessment when clinically indicated.