


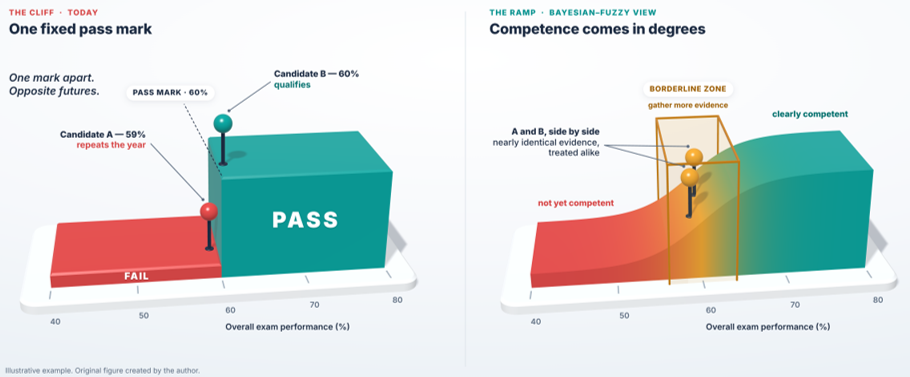
TWO MEDICAL STUDENTS walk out of the same final practical examination. The pass mark is 60 per cent. One scores 60 and, within months, will be caring for patients. The other scores 59 and must repeat the year. Ask the examiners whether a single mark truly separates a safe doctor from an unsafe one, and most would hesitate.
That hesitation is what this article is about. Every year, examiners meet candidates whose performance sits right on the edge: not clearly competent, not clearly incompetent. Traditionally, the system settles that doubt by ignoring it. A line is drawn, and everyone lands on one side of it. Mathematics offers a better option: describe the doubt honestly, measure it, and reduce it step by step until a fair decision is possible. The numbers here are illustrative; the dilemma is real.
When evidence points in different directions
Clinical examinations usually take the form of a circuit of short stations. At each one, a candidate might take a patient’s history, examine a patient, explain a diagnosis or carry out a procedure while an examiner watches. For most candidates, the picture is consistent. For a borderline candidate, it rarely is: confident communication at one station, a hesitant examination at the next, a nearly correct procedure at a third.
Examiners feel this uncertainty too. Research on high-stakes clinical examinations reports that examiners give ‘borderline’ grades precisely when they lack enough information for a clear pass or fail, that they feel less confident failing a student than passing one, and that their judgments can drift over a long examination day.3 A fixed cut-off hides all of this. It treats 59 and 60 as worlds apart, yet treats 60 and 95 as the same. It also hides how sure we are: a 60 built from consistent performance and a 60 assembled from wildly mixed observations receive the same verdict. The problem is not careless examiners. It is that a single number throws away exactly the information we need most in the hardest cases (Figure 1).
Two ideas that take doubt seriously
Two branches of mathematics, born two centuries apart, both begin by admitting uncertainty rather than ignoring it.
The first is fuzzy logic, which grew from the theory of fuzzy sets that Lotfi Zadeh introduced in 1965.2 Ordinary logic insists that a statement is either true or false; fuzzy logic allows degrees of truth. Is a temperature of 37.6 °C a fever? Is dusk day or night? Our natural answer, ‘partly’, is exactly what fuzzy logic puts into numbers. Instead of labelling performance at a station simply ‘pass’ or ‘fail’, it can be described as mostly competent with some gaps: a degree between 0 and 1. Clinical competence, like dusk, comes in shades.
The second is Bayesian reasoning, named after the eighteenth-century minister and mathematician Thomas Bayes. It describes how a belief should change as new evidence arrives. Doctors already reason this way: symptoms suggest several possible diagnoses, and each test result makes some more likely and others less so. Bayesian reasoning attaches numbers to that process, so each observation shifts our confidence in proportion to how informative it is.
Each idea solves half the problem. Fuzzy logic captures the nuance in every observation but does not say how confident we should be overall. Bayesian reasoning combines evidence powerfully but needs it in a usable form. Together they make a natural partnership: fuzzy logic can translate what examiners see into graded evidence, and Bayesian reasoning can combine that evidence into an overall probability that a candidate is genuinely competent, with an honest sense of how certain that probability is. My colleagues and I recently brought the two together in a hybrid approach to standard setting, the process of deciding where an examination’s pass standard should lie.1
Reaching a decision step by step Return to our 59-per-cent candidate; call her Meera. Under a fixed cut-off, her story ends in one line. In a Bayesian–fuzzy framework, it unfolds in four steps (Figure 2).

- Gather. Observations from every station, including checklist scores and examiners’ overall judgments, are kept rather than collapsed into one total.
- Grade. Fuzzy logic converts each observation into a degree of competence. Meera’s communication is strongly competent; her physical examination is only partly so.
- Update. Starting from a neutral position, the framework revises its confidence after every station. Clear evidence moves the needle a lot; ambiguous evidence moves it a little.
- Decide. If the evidence clearly points to competence, the candidate passes; if it clearly points the other way, she does not. If it remains genuinely mixed, the framework says so and recommends gathering more evidence first.
For Meera, six stations leave the evidence genuinely mixed. Instead of forcing a verdict, the framework recommends one extra station focused on physical examination. She performs it well, and her result moves firmly into the pass zone. Had that station revealed a real weakness, the framework would have supported a fail with the same confidence and equally clear reasons. That third option, ‘not sure yet’, is the heart of the approach. A fixed cut-off must push every candidate onto one side of the line, even when the evidence supports neither. The framework turns doubt into a structured next step instead, and every decision comes with its reasons: which observations counted, by how much, and why. A decision that can be explained is a decision that can be defended, to the candidate, to the institution and, ultimately, to patients.
Keeping human judgment in the process
No formula should decide a person’s future on its own, and this framework is not designed to. Its role is to support examiners by making their collective judgment more consistent, transparent and fair, not to replace them. The fuzzy grades encode what experienced clinicians regard as competent, and people still make the final call on borderline cases.
Real challenges remain. The framework is only as good as the observations fed into it, so examiner training and well-designed stations still matter. Institutions must agree in advance how much certainty a pass requires, which is a value judgment rather than a mathematical one. And the approach must be tested across medical schools, countries and examination formats before it can be widely trusted.
The opportunity reaches well beyond medicine. The same logic applies wherever people are judged against a standard using imperfect evidence: nursing and pharmacy licensing, professional certification, even recruitment. Wherever a single cut-off is asked to carry more weight than it can bear, an honest mathematics of doubt can help.








